FAI Surgery Rehabilitation - Part 2
In part one of this blog we highlighted the pre-operative and early postoperative phase of FAI surgery. Part two will expand on the middle-stage of rehab.
The middle-phase begins at achieving the exit criteria of the early postoperative phase: a manageable level of symptom irritability in the hip with activities of daily living, including walking, and the initial hip loading rehab exercises. At this stage, the individual has shown that they can return to their normal daily routine and still keep symptoms within tolerable ranges, and no worse into the next day. While it is normal to have symptoms in the hours or day following a higher volume or intensity of loading, we would like daily activities to be less of a contributor to keep the rehab program predictable.
Given the high level of variability in post-operative protocols and a lack of evidence on which approach is superior, we intend to describe our approach at MANA Performance Therapy and the rationale behind it.1-3 To start the middle-stage, our goal is to develop a two to three day per week plan that involves a gradual progression from symptom tolerance to work capacity to maximal strength. Symptom tolerance describes an exercise with the intention of gradually increasing the tissue’s ability to load at a higher intensity, volume, and/or frequency. Work capacity is a term that describes the “strength-endurance” attribute, commonly referring to repetition ranges from 6-15. Maximal strength can be defined as higher intensity exercises that result in the production of more force over time. It is important to note that different movement patterns in the hip will progress through these stages at different rates. For example, a common recommendation early on in the middle-phase of post-surgical FAI rehab is to slowly progress hip flexion exercise. Post-operative iliopsoas tendinopathy has been reported in 7-24% of cases, and can be a strong contributor to pain, slowing the overall rehab arc. It is unclear what the risk factors are for the development of an iliopsoas tendinopathy, but thought that a general “overuse” of the muscle group can contribute.4,5 This is one consideration for our exercise programming in the middle-phase of rehab, but we come back to several other questions to help with prioritization during this stage:
- What is the torque-generating potential of this movement pattern on the hip joint?
- What is the relevance of this movement pattern to their sporting movement?
- Do the deficits in this movement pattern seem to resolve naturally over time?
- How irritable does training this movement pattern make the hip?
These questions ultimately help guide the “how urgently should I train this movement pattern?” dilemma that can be difficult to answer during post-operative FAI rehab (See Figure 1).
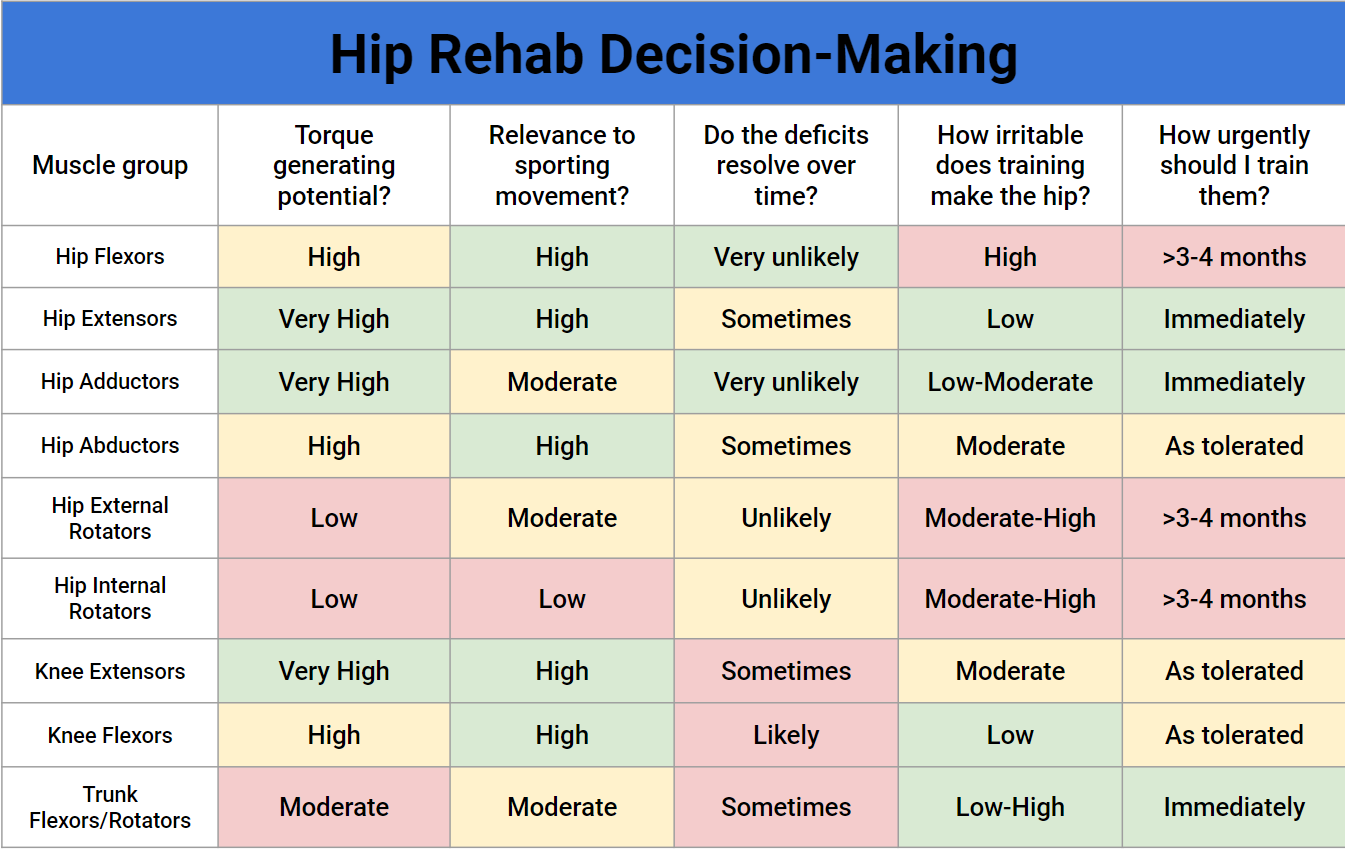
Figure 1: Considerations for exercise selection following FAI surgery
For context on how much torque-generating potential these movement patterns have on the hip, see Figure 2 based on normative data reported in the literature.6-9
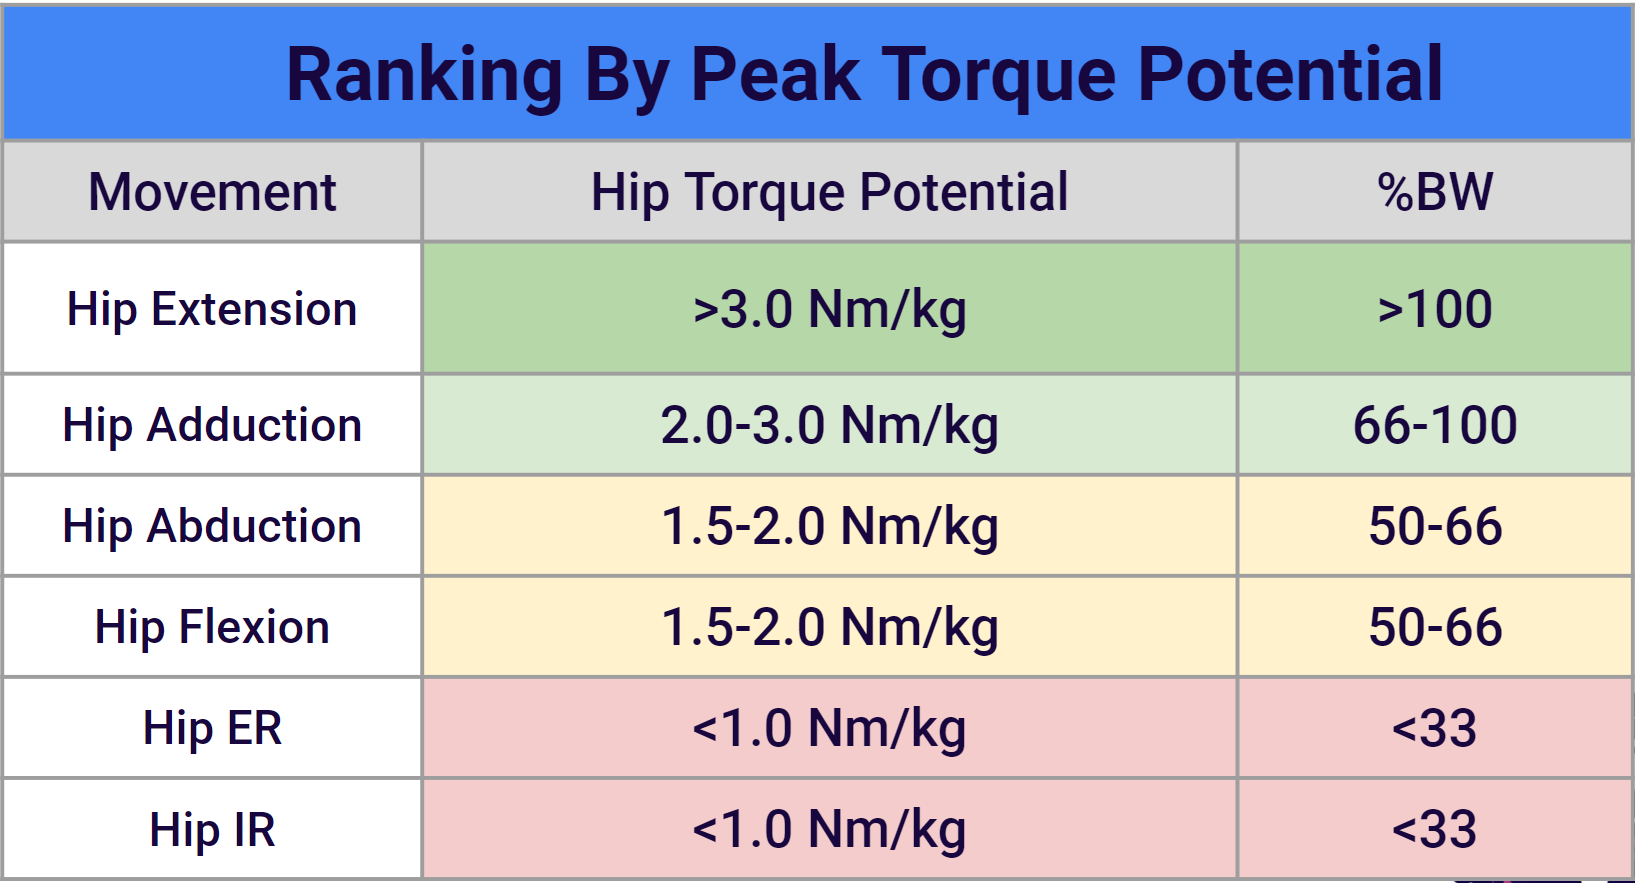
Figure 2: Hip movement pattern and respective peak torque potential
This can help contextualize why the goals of the middle-phase of rehab involve returning to typical lower body strength training exercises like the squat and deadlift, while placing an extra focus on frontal plane movements like hip adduction and abduction training. During this phase, the depth or range of motion of the exercise is a common variable to manipulate. Lower range of motion but high loaded exercises like isometric mid-thigh pulls, rack pulls, trap bar deadlifts, and pin squat variations are effective ways to drive force production adaptations while minimizing discomfort from approaching deeper hip flexion angles. These can be paired with higher range of motion and lower loaded exercises with the goal of improving symptom tolerance throughout the full range. Similarly, training for speed or rate of force production can follow a similar trajectory of fast through partial range and slow through large range. An example of a two day split demonstrating the goals of this stage can be seen in Figure 3.

Figure 3: Two day plan during months 2-3 following FAI surgery
In this example, the squat and hinge key exercises alternate between high load/low range of motion and low load/high range of motion, while the accessory movements focus on varying degrees of constrained hip adduction, abduction, and trunk resistance training. We can generally expect several months in this middle-phase to build the attributes needed for returning to sports performance training, with variability across individuals and sports.
Part three of this blog will discuss the return to sport stage of rehab following FAI surgery. If you're looking for guidance with hip pain or decisions on FAI surgery, please reach out!
References:
- Bistolfi A, Guidotti C, Aprato A, et al. Rehabilitation protocol after hip arthroscopy: a 2015-2020 systematic review. Am J Phys Med Rehabil. 2021;100(10):958-965.
- Cvetanovich GL, Lizzio V, Meta F, et al. Variability and comprehensiveness of north american online available physical therapy protocols following hip arthroscopy for femoroacetabular impingement and labral repair. Arthroscopy. 2017;33(11):1998-2005.
- Cheatham SW, Enseki KR, Kolber MJ. Postoperative rehabilitation after hip arthroscopy: a search for the evidence. J Sport Rehabil. 2015;24(4):413-418.
- Campbell A, Thompson K, Pham H, et al. The incidence and pattern of iliopsoas tendinitis following hip arthroscopy. Hip Int. 2021;31(4):542-547.
- Adib F, Johnson AJ, Hennrikus WL, Nasreddine A, Kocher M, Yen YM. Iliopsoas tendonitis after hip arthroscopy: prevalence, risk factors and treatment algorithm. J Hip Preserv Surg. 2018;5(4):362-369.
- Krantz MM, Åström M, Drake AM. Strength and fatigue measurements of the hip flexor and hip extensor muscles: test-retest reliability and limb dominance effect. Int J Sports Phys Ther. 2020;15(6):967-976.
- Thorborg K, Serner A, Petersen J, Madsen TM, Magnusson P, Hölmich P. Hip adduction and abduction strength profiles in elite soccer players: implications for clinical evaluation of hip adductor muscle recovery after injury. Am J Sports Med. 2011;39(1):121-126.
- Mosler AB, Crossley KM, Thorborg K, et al. Hip strength and range of motion: Normal values from a professional football league. J Sci Med Sport. 2017;20(4):339-343.
- Kemp JL, Schache AG, Makdissi M, Sims KJ, Crossley KM. Greater understanding of normal hip physical function may guide clinicians in providing targeted rehabilitation programmes. J Sci Med Sport. 2013;16(4):292-296.